
Breaking Through the Blind Spot: Reframing Idiopathic Intracranial Hypertension
IIH can look like migraine, tinnitus or an eye problem—until rising intracranial pressure puts vision at risk. Earlier recognition and coordinated care can change what happens next.
Persistent headaches. Ringing in the ears. Subtle changes in vision. Each can be easy to explain away on its own.
But sometimes those symptoms are connected by something more serious: idiopathic intracranial hypertension, or IIH, a condition in which pressure builds inside the skull and can threaten vision if it is not recognized and treated.
The problem is that IIH can initially resemble far more common conditions. Patients may spend months being treated for headache or other symptoms before the underlying pressure problem becomes clear.
“IIH is often misdiagnosed as a more benign disorder, like migraine, until visual symptoms escalate.”Ronald P. Benitez, MD · Atlantic Brain & Spine
The name describes the problem—even when the cause isn’t clear.
Idiopathic intracranial hypertension is sometimes called pseudotumor cerebri because its symptoms can resemble those of a brain tumor, even though no tumor is present.
The condition is defined by elevated pressure without an obvious mass or other direct cause.
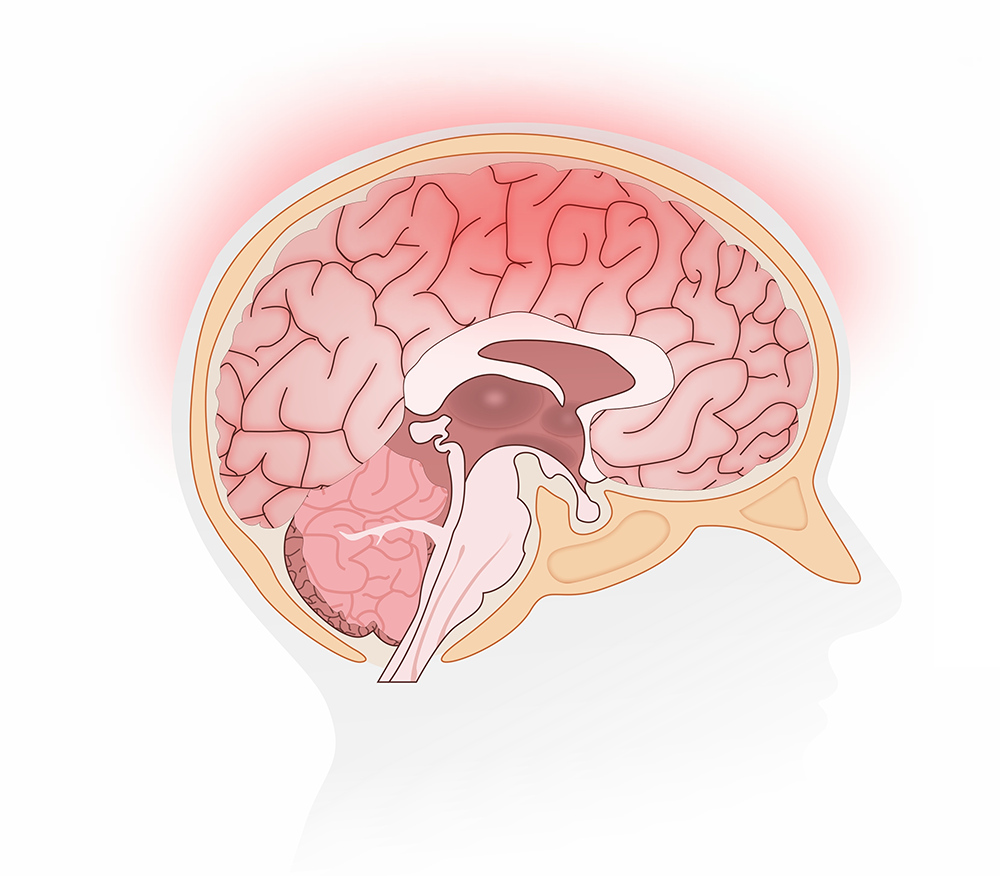
The pressure occurs within the fixed space surrounding the brain.
Increased intracranial pressure can produce headache, tinnitus and, critically, pressure on the optic nerves.
Elevated intracranial pressure can cause papilledema—swelling of the optic disc—which can ultimately lead to permanent vision loss if the underlying pressure is not addressed.
IIH can hide in symptoms that look like something else.
Headache is common. Visual changes can have many causes. Pulsatile tinnitus may initially seem unrelated. Taken one at a time, the symptoms of idiopathic intracranial hypertension can send patients down very different diagnostic paths.
The challenge is recognizing when those pieces belong together and determining whether elevated intracranial pressure is putting the optic nerves—and ultimately vision—at risk.
A common symptom that may initially be attributed to migraine or another headache disorder.
Blurred vision, transient visual obscurations or other changes may reflect pressure affecting the optic nerves.
A rhythmic whooshing sound that follows the heartbeat can be an important clue to altered intracranial venous flow.
Swelling of the optic nerve caused by elevated intracranial pressure is an especially important finding because of the potential threat to vision.
IIH is rarely a one-specialist problem.
Diagnosis and treatment often require clinicians to connect neurological symptoms, eye findings, intracranial pressure and the anatomy of the brain’s venous drainage system.
Ophthalmic evaluation
Eye examination and visual testing help determine whether elevated pressure is affecting the optic nerves and vision.
Neurological evaluation
Symptoms, examination and pressure-related findings help establish the clinical picture and guide treatment.
Neurovascular evaluation
Imaging can identify narrowing in the intracranial venous sinuses and determine whether venous outflow may be contributing.
There is no single treatment path for every patient with IIH.
Treatment depends on the severity of symptoms, the threat to vision, the patient’s response to medical therapy and whether venous outflow obstruction is playing a meaningful role.
Medical management
Medication and other non-procedural strategies may help reduce intracranial pressure and manage symptoms.
Protecting vision
When pressure threatens the optic nerves, treatment decisions become more urgent and preserving vision becomes a central priority.
Procedural options
For selected patients, surgical or endovascular treatment may be considered when medical management is insufficient or anatomy points to a treatable cause.
Where venous sinus stenting fits.
Some patients with IIH have significant narrowing of the intracranial venous sinuses, which can interfere with normal venous outflow and contribute to elevated intracranial pressure.
In carefully selected patients, venous sinus stenting can open the narrowed segment, improve venous drainage and reduce the pressure gradient across the stenosis.
The important distinction is that the presence of narrowing on an image alone does not determine whether a patient should receive a stent. The anatomy, symptoms, pressure measurements, vision and overall clinical picture all matter.
The goal is to identify patients whose venous anatomy and physiology indicate that improving venous outflow may meaningfully address the underlying pressure problem.

Better IIH care starts by connecting what each specialty sees.
IIH sits at the intersection of several specialties. An eye specialist may see papilledema. A neurologist may be treating headaches. Imaging may reveal venous sinus narrowing. A neurovascular specialist may be evaluating whether that narrowing is contributing to elevated intracranial pressure.
The problem is that patients do not experience those findings separately. They experience one condition—and the consequences when the pieces are not connected quickly enough.
Earlier recognition, coordinated evaluation and more consistent patient selection can help protect vision while identifying which patients may benefit from medical, surgical or endovascular treatment.
Building IIH care around the patient—not the specialty.
Ronald P. Benitez, MD, and his colleagues at Atlantic Brain & Spine are working toward a dedicated IIH center designed to bring the different parts of IIH care together.
The vision is a more coordinated pathway for patients with suspected IIH or papilledema: faster access to the appropriate specialists, greater consistency in how patients are evaluated, and better information for determining when advanced treatment such as venous sinus stenting should be considered.
Faster evaluation
Expedited consultation for patients with suspected IIH or papilledema, particularly when vision may be at risk.
Connected specialists
Bringing eye, neurological, imaging and neurovascular perspectives together around the same patient.
Better data
Tracking outcomes and refining which patients are most likely to benefit from treatments such as venous sinus stenting.
What coordinated IIH care can bring together.
The specialists involved will vary by patient, but IIH often requires information from several disciplines to understand the complete clinical picture.
Papilledema, optic nerve health and visual function.
Headache, neurological symptoms and medical management.
Structural and venous imaging that helps define the anatomy.
Evaluating venous stenosis and whether intervention may help.
The next breakthrough may happen before treatment ever begins.
Advanced treatments matter, but they can only help patients who reach the right diagnosis. Improving IIH care also means helping clinicians recognize the pattern sooner—before prolonged symptoms or pressure on the optic nerves leads to permanent harm.
Headache, visual changes, pulsatile tinnitus and papilledema may be more meaningful when considered together.
Papilledema is not simply another symptom. Persistent pressure on the optic nerves can threaten permanent vision loss.
Coordinating eye findings, neurological symptoms, intracranial pressure and venous anatomy can reveal a more complete picture.
“As neurosurgeons, we must lead the effort to identify IIH sooner, educate our clinical peers, and ensure timely intervention before permanent damage occurs.”Ronald P. Benitez, MD · Atlantic Brain & Spine
Have IIH, papilledema or venous sinus stenosis?
Atlantic Brain & Spine evaluates patients with complex neurovascular conditions, including those seeking another perspective on IIH or whether venous sinus stenting may be appropriate.
